
Beta-blockers are a staple of both pharmacology questions and integrated systems questions on USMLE Step 1. Whether the question is about cardiac pharmacology, autonomic pharmacology, or clinical scenarios involving hypertension, heart failure, or glaucoma, understanding beta-blocker selectivity helps you identify the correct drug and predict its effects.
In this blog, we'll break down:
The difference between β₁- and β₂-adrenergic receptors
Which beta-blockers block which receptor types
Classic clinical uses and important drug distinctions
High-yield adverse effects and contraindications
Clinical scenarios you'll recognize on test day
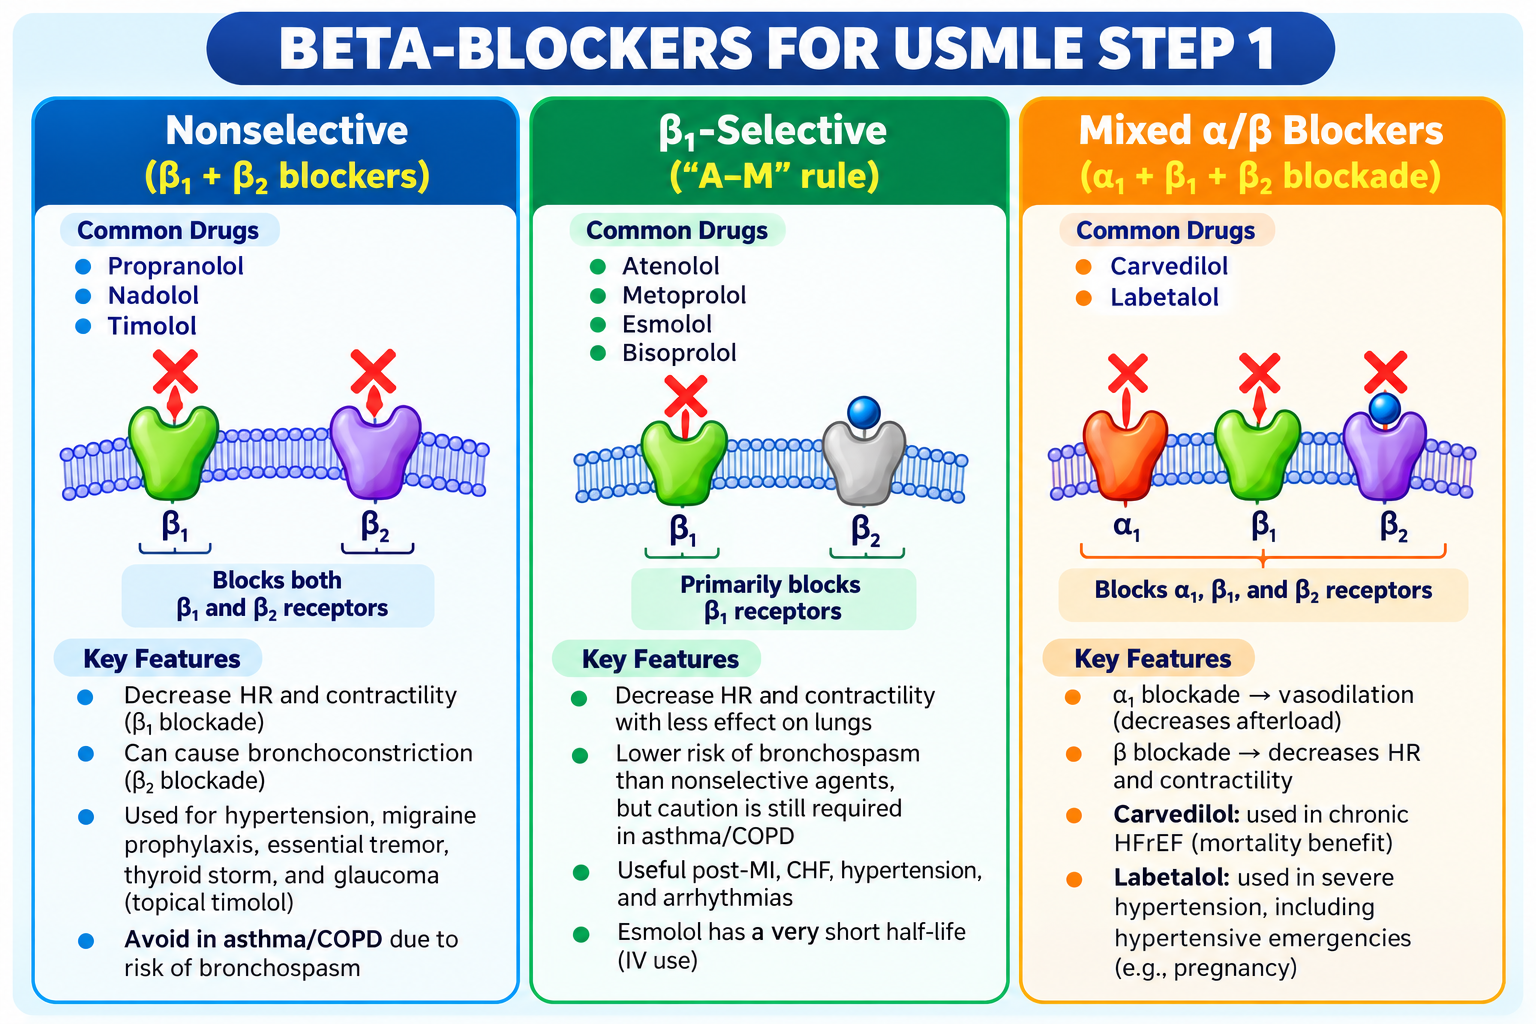
🔄 Beta Receptor Basics
| Receptor | Main Locations | Effect of Activation |
|---|---|---|
| β₁ | Heart, kidney juxtaglomerular cells | Increases heart rate, contractility, conduction, and renin release |
| β₂ | Bronchial smooth muscle, vascular smooth muscle, liver | Promotes bronchodilation, vasodilation, and glycogenolysis |
| α₁ | Vascular smooth muscle | Causes vasoconstriction |
USMLE takeaway: Blocking β₁ receptors reduces cardiac activity and renin release. Blocking β₂ receptors can cause bronchoconstriction, making nonselective beta-blockers particularly concerning in patients with asthma.
💊 Types of Beta-Blockers
1. Nonselective beta-blockers (β₁ and β₂)
Examples: Propranolol, nadolol, timolol.
These medications block both β₁ and β₂ receptors.
Clinical uses:
Propranolol: essential tremor, migraine prevention, certain tachyarrhythmias, and symptomatic control of hyperthyroidism.
Nadolol and propranolol: prevention of variceal bleeding in selected patients with portal hypertension.
Topical timolol: reduction of intraocular pressure in glaucoma.
Important caution: Nonselective beta-blockers can cause bronchospasm by blocking β₂-mediated bronchodilation. They are generally avoided in patients with asthma.
2. β₁-Selective Beta-Blockers (Cardioselective)
Examples: Atenolol, metoprolol, esmolol, bisoprolol, acebutolol.
These medications preferentially block β₁ receptors, particularly at lower doses.
Clinical uses:
Metoprolol succinate and bisoprolol: chronic, stable heart failure with reduced ejection fraction (HFrEF).
Metoprolol: heart rate control in selected tachyarrhythmias.
Esmolol: short-term intravenous heart rate control because of its very short duration of action.
Atenolol: treatment of selected patients with hypertension or angina.
Important caution: β₁ selectivity is dose-dependent and not absolute. Cardioselective agents generally have a lower risk of bronchospasm than nonselective agents, but caution is still necessary in asthma.
Mnemonic: A–M can help recall Atenolol and Metoprolol, but it does not cover every β₁-selective drug. Esmolol, bisoprolol, and acebutolol are also important examples.
3. Mixed α₁/β Blockers
Examples: Carvedilol and labetalol.
These drugs block β₁ and β₂ receptors while also antagonizing α₁ receptors.
Mechanism:
β₁ blockade: decreases heart rate, contractility, and renin release.
α₁ blockade: causes peripheral vasodilation.
β₂ blockade: can increase bronchospasm risk.
Clinical uses:
Carvedilol: chronic, stable HFrEF and hypertension.
Labetalol: severe hypertension, including selected hypertensive emergencies and hypertension during pregnancy.
USMLE takeaway: Mixed α₁/β blockers reduce blood pressure through both decreased cardiac sympathetic effects and peripheral vasodilation.
🚑 Step 1 Clinical Scenarios
📌 Scenario 1: Asthma + Hypertension
A patient with asthma requires treatment for hypertension.
Key concept: Nonselective beta-blockers, such as propranolol, may cause bronchospasm through β₂ blockade.
A cardioselective β₁ blocker may be considered when there is a compelling indication for beta-blockade, but it is not automatically the preferred first-line antihypertensive.
📌 Scenario 2: Chronic HFrEF
A patient with stable heart failure and reduced ejection fraction needs long-term guideline-directed therapy.
High-yield drugs: Metoprolol succinate, bisoprolol, and carvedilol.
These specific beta-blockers have demonstrated mortality benefits in appropriate HFrEF patients.
Exam trap: Metoprolol succinate (extended-release), not metoprolol tartrate, is the formulation with established HFrEF mortality benefit.
📌 Scenario 3: Glaucoma
A patient is prescribed timolol eye drops.
Mechanism: Topical timolol lowers intraocular pressure by reducing aqueous humor production in the ciliary epithelium.
Exam trap: Even topical beta-blockers may be systemically absorbed and cause bradycardia or bronchospasm.
📌 Scenario 4: Thyroid Storm
A patient develops severe tachycardia, tremor, and other manifestations of thyroid storm.
Drug: Propranolol.
Mechanism: Beta-receptor blockade controls adrenergic symptoms. At higher doses, propranolol also inhibits peripheral conversion of T4 to T3.
Exam trap: Propranolol is supportive treatment, not definitive therapy for thyroid storm.
📌 Scenario 5: Hypertensive Emergency During Pregnancy
A pregnant patient develops severe hypertension requiring urgent treatment.
Drug: Intravenous labetalol is one commonly used option.
Mechanism: Combined α₁ and β blockade lowers blood pressure.
Exam trap: Labetalol is not the only option; intravenous hydralazine and oral immediate-release nifedipine are also used in appropriate circumstances.
❗ High-Yield Side Effects
Beta-blockers have predictable adverse effects based on their receptor targets.
Adverse effect
Pharmacologic explanation
Bradycardia
β₁ blockade decreases sinoatrial node activity
Hypotension
Reduced cardiac output and renin release; α₁ blockade contributes with mixed agents
Fatigue and exercise intolerance
Reduced sympathetic cardiac response
Bronchospasm
β₂ blockade reduces bronchodilation
Masking hypoglycemia
Adrenergic warning signs, especially tachycardia, may be masked
AV conduction slowing
β₁ blockade reduces atrioventricular nodal conduction
Rebound tachycardia or angina
Abrupt withdrawal after chronic use can increase adrenergic effects
Important cautions: Beta-blockers require special consideration in significant bradycardia, advanced AV block without pacing, acute decompensated heart failure, and bronchospastic disease.
🧠 Pro Tip: Know These Mnemonics
Nonselective Beta-Blockers: P–N–T
P — Propranolol
N — Nadolol
T — Timolol
All three block β₁ and β₂ receptors.
β₁-Selective: Remember A–M, Then Add the Others
A — Atenolol
M — Metoprolol
Also remember esmolol, bisoprolol, and acebutolol.
Mixed α₁/β Blockers: C–L
C — Carvedilol
L — Labetalol
Both have α₁-blocking activity in addition to beta blockade.
Quick memory rule: β₁ = one heart; β₂ = two lungs. This is a simplified mnemonic, not a complete description of receptor distribution.
🎯 Test Your Knowledge
Question: A patient with glaucoma receives timolol eye drops and subsequently develops wheezing and bradycardia. Which receptor effects best explain these findings?
A. α₁ blockade and β₁ stimulation
B. β₂ blockade and β₁ blockade
C. β₂ stimulation and α₁ blockade
D. Selective β₁ stimulation
Correct answer: B.
Timolol is a nonselective beta-blocker. β₂ blockade can cause bronchospasm, while β₁ blockade can cause bradycardia. Systemic absorption can occur even with ophthalmic administration.
📚 Study Smarter With King of the Curve
Want to quiz yourself on beta-blocker selectivity, mechanisms, and side effects?
Practice with King of the Curve's adaptive question bank and multiple-choice practice tools to reinforce your understanding of high-yield pharmacology concepts.
Explore MCAT and other exam-preparation resources at King of the Curve
🎯 Call-To-Action
Want to quiz yourself on selectivity, mechanism, and side effects?
🎓 Practice with KOTC’s Adaptive QBank and Multiplayer Mode:
🔗 https://kingofthecurve.org/trial-sessions
💎 Or unlock the full visual pharmacology set now:
🔗 https://kingofthecurve.org/free-lifetime

Frequently Asked Questions (FAQs)
-
Aim for 4-6 focused hours, ensuring you incorporate breaks to avoid burnout.
-
Practice mindfulness techniques, take practice exams under realistic conditions, and maintain a balanced lifestyle.
-
Set short-term goals, seek support from mentors, and reward yourself for small achievements.
-
Regular exercise improves focus, reduces stress, and enhances overall mental clarity.
-
KOTC offers personalized learning tools, gamification features, and adaptive question banks to help students stay on track without burnout.
